Atrial fibrillation with rapid ventricular response
Also called A-fib with RVR, rapid A-fib.
The same irregularly irregular, P-less rhythm as atrial fibrillation, but the ventricles are being driven fast, well over 100. The irregularity is harder to see at speed, so march out the R-R intervals.
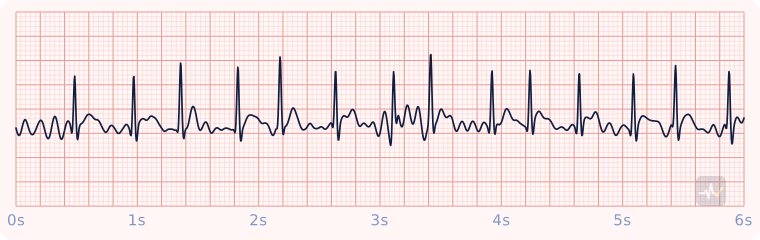
How to identify Atrial fibrillation with rapid ventricular response
- Rate
- Ventricular rate well over 100
- Rhythm
- Irregularly irregular
- P waves
- None, just a chaotic fibrillatory baseline
- PR interval
- None
- QRS
- Under 0.12 s
- Clincher
- Irregularly irregular and fast. March out the R-R intervals, the irregularity hides at speed.
Rhythms it gets mistaken for
Atrial fibrillation with rapid ventricular response vs Multifocal atrial tachycardia
Atrial fibrillation with rapid ventricular response has no P waves, only a wavy, chaotic baseline. With multifocal atrial tachycardia you would see P waves of at least three different shapes.
Atrial fibrillation with rapid ventricular response vs Supraventricular tachycardia
Atrial fibrillation with rapid ventricular response has no P waves, only a wavy, chaotic baseline. With SVT you would see no P wave you can see at all.
Atrial fibrillation with rapid ventricular response vs Atrial fibrillation
Atrial fibrillation with rapid ventricular response has a rate over 100/min. With A-fib you would see a rate of 60-100/min.
Treatment by certification level
Open your level. Treat the patient, not the strip.
Paramedic
Stable
Stable: treat the ventricular rate, if it needs treating at all.
- It is the ventricular rate, not the atrial rate, that decides treatment. A normal ventricular rate in a stable patient needs no rate drug and no cardioversion.
- Fast and stable: rate control with diltiazem 0.25 mg/kg IV over 2 minutes, then 0.35 mg/kg if the response is inadequate, or a beta blocker per protocol.
- No diltiazem or beta blocker with an accessory pathway (WPW), severe hypotension, or a rhythm whose origin is uncertain.
- Onset more than 48 hours ago or unknown: do not convert a stable patient. A clot may have formed in the atrium.
Unstable
Unstable with a fast ventricular rate: synchronized cardioversion.
- Sedate the conscious patient if time and blood pressure allow.
- Synchronized cardioversion starting at 120-200 J; escalate if it fails.
Unstable means hypotension, altered mental status, signs of shock, ischemic chest pain, or acute heart failure caused by the rate.
AEMT
Stable
Pulse present and stable.
- Oxygen only if hypoxic or short of breath, IV access, monitoring.
- Acquire and transmit a 12-lead ECG. Interpreting it is a Paramedic skill.
- Transport and reassess. Request a paramedic if the patient worsens.
Unstable
Unstable with a pulse.
- Oxygen if hypoxic, IV access, close monitoring.
- Expedited transport, with a paramedic intercept if that is genuinely faster than reaching the hospital.
Synchronized cardioversion and pacing are Paramedic-only, so the AEMT has no electrical option for a patient with a pulse. Never put the AED on this patient.
EMT
Stable
Pulse present: assess and support.
- Treat the patient, not the rhythm name: airway, breathing, circulation, vital signs.
- Oxygen if the SpO2 is under 94%, the patient is short of breath, or shows signs of shock.
- Request ALS and transport promptly. Reassess on the way.
An AED goes only on a patient who is unresponsive, not breathing and pulseless. It cannot feel a pulse, so on a patient with a pulse it can advise a shock that would do harm.
Unstable
Pulse present but poorly perfusing: this patient needs ALS fast.
- Treat the patient, not the rhythm name: airway, breathing, circulation, vital signs.
- Oxygen if the SpO2 is under 94%, the patient is short of breath, or shows signs of shock.
- Request ALS and transport promptly. Reassess on the way.
An AED goes only on a patient who is unresponsive, not breathing and pulseless. It cannot feel a pulse, so on a patient with a pulse it can advise a shock that would do harm.