2nd-degree type I (Wenckebach)
Also called second-degree AV block type I, Mobitz I, Wenckebach.
The PR interval lengthens beat after beat until one P wave is not conducted and its QRS drops, then the cycle restarts. Longer, longer, longer, drop. Usually nodal and usually benign.
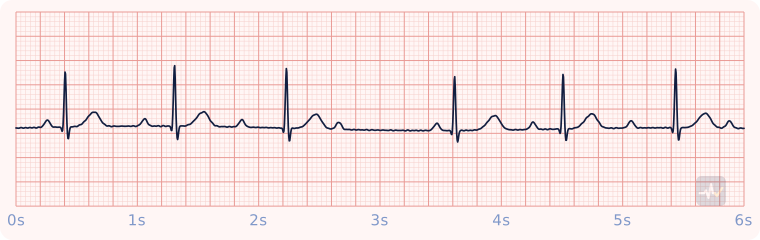
How to identify 2nd-degree type I (Wenckebach)
- Rate
- Ventricular slower than atrial
- Rhythm
- Regularly irregular, in groups
- P waves
- Regular, more P waves than QRS complexes
- PR interval
- Lengthens beat after beat until a QRS drops
- QRS
- Under 0.12 s
- Clincher
- Longer, longer, longer, drop. Usually nodal and usually benign.
- Memory trick
- "Longer, longer, drop, you have a Wenckebach." The PR gets longer every beat, then a QRS drops. That stretching PR is your warning.
Rhythms it gets mistaken for
2nd-degree type I (Wenckebach) vs 2nd-degree type II (Mobitz II)
2nd-degree type I (Wenckebach) has a PR interval that gets longer beat after beat until a QRS drops. With Mobitz II you would see a PR interval that stays the same, then a QRS that drops without warning.
2nd-degree type I (Wenckebach) vs 1st-degree AV block
2nd-degree type I (Wenckebach) has regular P waves, with more P waves than QRS complexes. With 1st-degree block you would see one upright P wave before every QRS, all the same shape.
2nd-degree type I (Wenckebach) vs 3rd-degree (complete) AV block
2nd-degree type I (Wenckebach) has a PR interval that gets longer beat after beat until a QRS drops. With 3rd-degree block you would see no relationship between the P waves and the QRS complexes. A narrow QRS means the signal came from above the ventricles.
Treatment by certification level
Open your level. Treat the patient, not the strip.
Paramedic
Stable
Asymptomatic: watch it, do not treat the number.
- Monitor, IV access, transport and reassess.
- No atropine, pacing or infusion for the asymptomatic patient.
- If it becomes symptomatic (hypotension, altered mental status, signs of shock, ischemic chest pain, acute heart failure): atropine 1 mg every 3-5 minutes (maximum 3 mg), then transcutaneous pacing, or dopamine 5-20 mcg/kg/min or epinephrine 2-10 mcg/min.
Unstable
Symptomatic bradycardia: atropine, then pacing or an infusion.
- Oxygenation and ventilation support, IV access, monitor.
- Atropine 1 mg IV every 3-5 minutes, maximum 3 mg.
- No response: transcutaneous pacing (rate 60-80, mA up until capture, then slightly above). Confirm mechanical capture with a femoral pulse. Sedation and analgesia.
- Or a chronotropic infusion: dopamine 5-20 mcg/kg/min, or epinephrine 2-10 mcg/min, titrated to effect.
- Look for and treat the cause: hypoxia first, then medications and high potassium.
AEMT
Stable
Pulse present and stable.
- Oxygen only if hypoxic or short of breath, IV access, monitoring.
- Acquire and transmit a 12-lead ECG. Interpreting it is a Paramedic skill.
- Transport and reassess. Request a paramedic if the patient worsens.
Unstable
Symptomatic bradycardia with a pulse.
- Support oxygenation and ventilation, establish IV access, and move the patient.
- Expedited transport, with a paramedic intercept if that is genuinely faster than reaching the hospital.
Synchronized cardioversion and pacing are Paramedic-only, so the AEMT has no electrical option for a patient with a pulse. Never put the AED on this patient.
EMT
Stable
Pulse present: assess and support.
- Treat the patient, not the rhythm name: airway, breathing, circulation, vital signs.
- Oxygen if the SpO2 is under 94%, the patient is short of breath, or shows signs of shock.
- Request ALS and transport promptly. Reassess on the way.
An AED goes only on a patient who is unresponsive, not breathing and pulseless. It cannot feel a pulse, so on a patient with a pulse it can advise a shock that would do harm.
Unstable
Pulse present but poorly perfusing: this patient needs ALS fast.
- Treat the patient, not the rhythm name: airway, breathing, circulation, vital signs.
- Oxygen if the SpO2 is under 94%, the patient is short of breath, or shows signs of shock.
- Request ALS and transport promptly. Reassess on the way.
An AED goes only on a patient who is unresponsive, not breathing and pulseless. It cannot feel a pulse, so on a patient with a pulse it can advise a shock that would do harm.