2nd-degree type II (Mobitz II)
Also called second-degree AV block type II, Mobitz II.
The PR on conducted beats is constant and never lengthens, yet P waves are intermittently not conducted and a QRS drops without warning. It sits below the AV node and can progress abruptly to complete block.
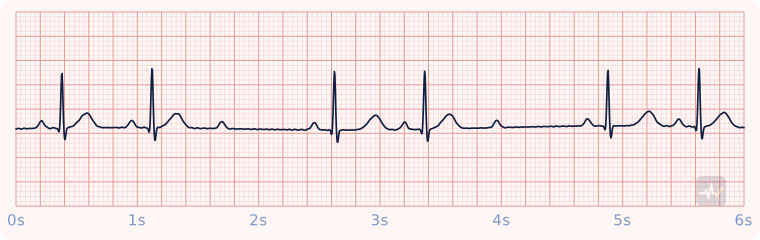
How to identify 2nd-degree type II (Mobitz II)
- Rate
- Ventricular slower than atrial
- Rhythm
- Irregular where beats drop
- P waves
- Regular, more P waves than QRS complexes
- PR interval
- Constant on every conducted beat
- QRS
- Narrow here; can be wide
- Clincher
- A constant PR, then a QRS drops without warning. It sits below the node and can progress to complete block.
Rhythms it gets mistaken for
2nd-degree type II (Mobitz II) vs 2nd-degree type I (Wenckebach)
2nd-degree type II (Mobitz II) has a PR interval that stays the same, then a QRS that drops without warning. With Wenckebach you would see a PR interval that gets longer beat after beat until a QRS drops.
2nd-degree type II (Mobitz II) vs 3rd-degree (complete) AV block
2nd-degree type II (Mobitz II) has a PR interval that stays the same, then a QRS that drops without warning. With 3rd-degree block you would see no relationship between the P waves and the QRS complexes. A narrow QRS means the signal came from above the ventricles.
2nd-degree type II (Mobitz II) vs 1st-degree AV block
2nd-degree type II (Mobitz II) has regular P waves, with more P waves than QRS complexes. With 1st-degree block you would see one upright P wave before every QRS, all the same shape.
Treatment by certification level
Open your level. Treat the patient, not the strip.
Paramedic
Stable
Stable, but watch it closely.
- Monitor, IV access, transport and reassess.
- This block can progress abruptly to complete block. Put the pads on now so pacing is ready.
- If it becomes symptomatic, go to pacing or dopamine 5-20 mcg/kg/min, or epinephrine 2-10 mcg/min, titrated to effect. Do not rely on atropine: the block sits below where it acts.
Unstable
Symptomatic high-grade block: go to pacing.
- Do not rely on atropine: the block sits below where it acts. Atropine 1 mg may be tried while the pads go on, but it never delays pacing.
- Transcutaneous pacing (rate 60-80, mA up until capture, then slightly above). Confirm mechanical capture with a femoral pulse, not a carotid.
- Sedation and analgesia; recheck the blood pressure once captured.
- No capture or still poorly perfusing: dopamine 5-20 mcg/kg/min, or epinephrine 2-10 mcg/min, titrated to effect.
- Expert consultation: this patient may need a transvenous pacer.
AEMT
Stable
Pulse present and stable.
- Oxygen only if hypoxic or short of breath, IV access, monitoring.
- Acquire and transmit a 12-lead ECG. Interpreting it is a Paramedic skill.
- Transport and reassess. Request a paramedic if the patient worsens.
Unstable
Symptomatic bradycardia with a pulse.
- Support oxygenation and ventilation, establish IV access, and move the patient.
- Expedited transport, with a paramedic intercept if that is genuinely faster than reaching the hospital.
Synchronized cardioversion and pacing are Paramedic-only, so the AEMT has no electrical option for a patient with a pulse. Never put the AED on this patient.
EMT
Stable
Pulse present: assess and support.
- Treat the patient, not the rhythm name: airway, breathing, circulation, vital signs.
- Oxygen if the SpO2 is under 94%, the patient is short of breath, or shows signs of shock.
- Request ALS and transport promptly. Reassess on the way.
An AED goes only on a patient who is unresponsive, not breathing and pulseless. It cannot feel a pulse, so on a patient with a pulse it can advise a shock that would do harm.
Unstable
Pulse present but poorly perfusing: this patient needs ALS fast.
- Treat the patient, not the rhythm name: airway, breathing, circulation, vital signs.
- Oxygen if the SpO2 is under 94%, the patient is short of breath, or shows signs of shock.
- Request ALS and transport promptly. Reassess on the way.
An AED goes only on a patient who is unresponsive, not breathing and pulseless. It cannot feel a pulse, so on a patient with a pulse it can advise a shock that would do harm.